Shoulder Pain, Arlington Texas
Shoulder Pain: Why The Shoulder Blade Gets Examined Too
The short answer
Most shoulder pain that responds to conservative care involves the rotator cuff and the way the shoulder blade moves underneath it. The blade is the base the arm swings from, so if it stops rotating properly the joint runs out of clearance and the tendons underneath take the load. Treatment is hands-on work plus a strength programme. The honest position is that the best trial evidence shows a modest benefit rather than a dramatic one, and that is said here rather than hidden.
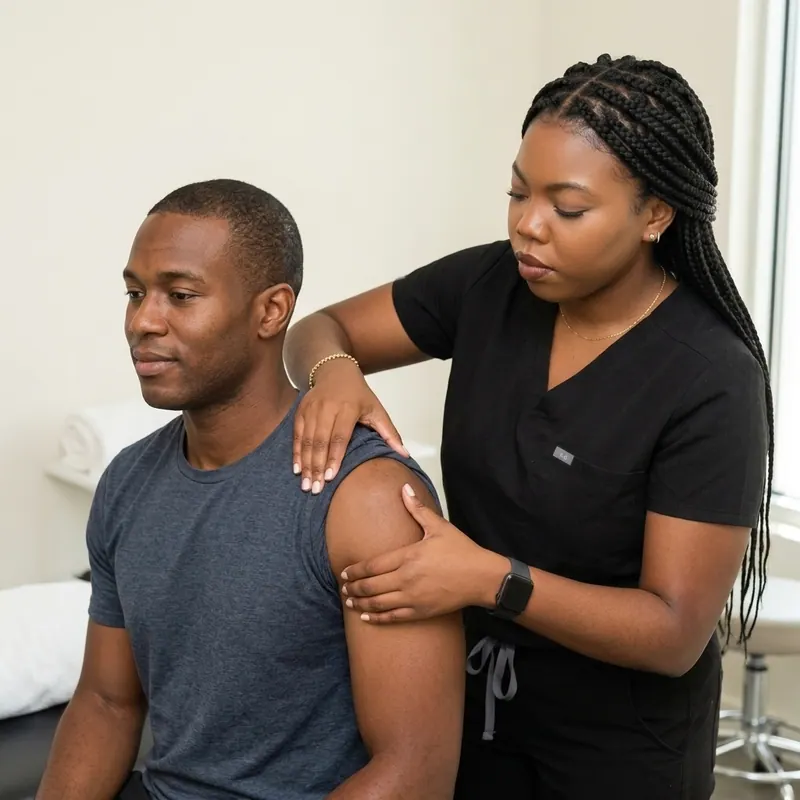
What Is Actually Happening
The Arm Swings From A Base That Has To Move
The shoulder blade is not a fixed anchor. It rotates through every overhead reach, and when it stops the tendons pay for it.
Raising your arm above your head is not one joint doing one thing. The ball and socket lifts the arm, and at the same time the shoulder blade rotates upward across the back of the ribs to keep the roof of the joint out of the way. Those two movements are supposed to be paired. When the blade stops contributing its share, usually because the muscles holding it have stopped working properly or because the mid back has stopped rotating, the space the rotator cuff tendons run through gets smaller at exactly the moment they are working hardest.
That is why the classic story is so consistent: fine at your sides, painful reaching overhead, painful reaching behind you into a coat, and worst of all lying on it at night. It is also why treating only the sore spot tends to buy a few comfortable weeks rather than a lasting change.
- How the blade rotates and sets when you lift the arm
- Whether the mid back is contributing rotation or has stopped
- Rotator cuff strength tested through range, not just at rest
- Whether the upper neck refers into the shoulder as well
- What the arm is asked to do at your work and in your training
What The Research Says
A Modest Benefit, Reported Honestly
Cochrane Database of Systematic Reviews, 2016 (Page and colleagues), manual therapy and exercise for rotator cuff disease: sixty trials covering 3,620 participants. In the highest quality trial, comparing manual therapy plus exercise against a placebo, 57 percent of participants reported treatment success against 41 percent on placebo, a difference the authors describe as uncertain because the confidence interval crosses no effect. Across five further trials there were no important differences between manual therapy with exercise and a steroid injection on pain, function or quality of life from four weeks out to twelve months. Adverse events were more common with treatment and were mild, mostly short lived soreness afterwards.
What this means in plain terms: this is worth doing and it is not a miracle. The useful finding is the second one. Hands-on treatment and exercise performed about as well as an injection over the following year, without the injection. That is a genuine option rather than a claim.
Full text: Manual therapy and exercise for rotator cuff disease, Cochrane Database of Systematic Reviews 2016.
There is a power rack and a cable machine in this building, which is unusual in an Arlington chiropractic clinic. That matters for a shoulder, because the treatment the evidence supports is a progressive strength programme and a programme has to be loaded and checked rather than described.
The Wider Picture
Sometimes The Shoulder Is Not The Problem
Pain felt in the shoulder does not always start there. The nerves supplying the arm leave the spine in the lower neck, so an irritated root can be felt in the shoulder and down the arm while the joint itself examines clean. Pain that travels below the elbow, or comes with pins and needles or weakness in the hand, points that way. So the neck gets examined on a shoulder complaint as a matter of routine, not as an extra.
Some shoulder problems are surgical, and some are not ours. A full thickness tear after a fall, a frozen shoulder well into its stiff phase, or an inflammatory arthritis all behave differently and get referred rather than treated anyway. Applied kinesiology is used here to test how the shoulder holds up under load muscle by muscle, which is useful for telling a weak shoulder from a painful one. It is part of an examination and it is not a diagnostic test on its own.
Read This First
When A Shoulder Needs A Doctor First
If You Notice Any of These Warning Signs, Please Seek Emergency Room Care Right Away.
- You cannot lift the arm at all after a fall or a collision, or the shoulder looks out of shape
- Shoulder pain following any significant trauma, or a suspected fracture or dislocation
- A hot, red, swollen joint, particularly alongside a fever
- Weakness that is getting worse, or numbness spreading into the hand
- New shoulder pain with a history of cancer, or with unexplained weight loss
- Shoulder pain with chest tightness, breathlessness or sweating, which needs emergency care immediately
There is no imaging in this building, so an X ray or an MRI means a referral rather than a guess. Call 817-800-7136 and describe what happened.
Common Questions
Shoulder Pain, Asked And Answered
Why would a chiropractor treat a shoulder?
Because the arm swings from the shoulder blade, the blade sits on the ribs, and the ribs and mid back have to rotate for any of it to work. Those are joints. Examining them alongside the shoulder itself is the whole argument for taking longer over it.
Is it a rotator cuff tear?
Sometimes, and a partial tear often does well with a strength programme. A full thickness tear after a fall behaves differently and is a surgical conversation. The examination is aimed at telling those apart, and if it points at a scan you get referred for one.
How long does it take?
Shoulders are slower than backs. Several weeks to a few months of progressive loading is normal, and the strength work is the part that decides the outcome. Anyone promising a quick result on a shoulder is guessing.
Should I rest it?
Complete rest tends to settle the pain and lose the strength, which is how shoulders get stiff. The usual approach is to keep it moving within what it tolerates while the loading is built back up.
Is an injection better?
The Cochrane review found no important differences between manual therapy with exercise and a steroid injection on pain, function or quality of life from four weeks out to twelve months. Injections have their place, and this is a reasonable thing to try first.
Do you take insurance for this?
Insurance and paying directly both work. Call 817-800-7136 and ask before you book, and you will be told how it works in your case. Appointments only, so a visit has to be booked.
Sources
Where The Numbers On This Page Come From
- Manual therapy and exercise for rotator cuff disease. Page MJ, Green S, McBain B, Surace SJ, Deitch J, Lyttle N, Mrocki MA, Buchbinder R. Cochrane Database of Systematic Reviews 2016, Issue 6, CD012224. Sixty trials, 3,620 participants. Source of the 57 percent against 41 percent treatment success figure, the absence of important differences against glucocorticoid injection from four weeks to twelve months, and the mild short term nature of the adverse events.
Get The Shoulder And The Blade Examined Together
Call and describe which movements hurt, or book online and pick a time.
3825 W Green Oaks Blvd, Suite 710, Arlington, TX 76016. Appointments only.